The Ulutas Medical Journal · ISSN 2149-0430 (print), 2149-388X (online) · https://www.ulutasmedicaljournal.com/?mno=75583
Original Article · Open access
Evaluation of Plasma Selenium, Zinc and Malondialdehyde Levels in Newly Diagnosed Preeclamptic Women at A Teaching Hospital
Also available in: العربية · Türkçe · 中文
- Department of Chemical Pathology, Chukwuemeka Odumegwu Ojukwu University, Awka, Anambra State, Nigeria ROR
- Department of Chemical Pathology, Nnamdi Azikiwe University, Nnewi, Anambra State, Nigeria ROR
Abstract
- Introduction
- Preeclampsia is a clinical condition unique to humans which forms a major part of hypertensive disorders in pregnancy. Although its exact etiology remains unknown, an imbalance between lipid peroxides and antioxidants is implicated. The study aimed to evaluate plasma selenium, zinc, and malondialdehyde (MDA) levels in newly diagnosed preeclamptic women attending antenatal visits at Chukwuemeka Odumegwu Ojukwu University Teaching Hospital (COOUTH), Awka in Anambra State.
- Materials and Methods
- A total of 81 female participants were recruited and grouped into three (A, B, and C) comprising 21 newly diagnosed preeclamptic women, 30 healthy pregnant control, and 30 non-pregnant control participants respectively.
- Results
- The newly diagnosed preeclamptics had significantly lower plasma selenium levels when compared with the healthy pregnant and non-pregnant controls (p<0.05). The plasma zinc level in the preeclamptics did not differ significantly from the level in healthy pregnant women (p>0.05), it was however significantly lower in the preeclamptics and healthy pregnant women when compared with the non-pregnant women (p<0.05). Plasma MDA level was significantly elevated in the preeclamptics compared to the healthy pregnant and non-pregnant control participants (p<0.05).
- Conclusion
- Newly diagnosed preeclamptics have lower plasma selenium and zinc levels with higher plasma MDA levels, and additional sources of these micronutrients may be required.
Keywords
Full text
Introduction
Preeclampsia is a human pregnancy specific disorder which forms a major part of hyper tensive disorders (1). It presents with elevation of blood pressure to ≥140/90 mmHg and significant proteinuria of ≥0.3g/day or ≥30mg /mmol of urinary creatinine in random sample after 20 weeks of gestational age (2). It may as well occur as late as 4 - 6 weeks postpartum (3). It is a major cause of long term maternal and perinatal mortality and morbidity worldwide (4, 5). In as much as preeclampsia remains a threat to pregnancy, its exact aetiology and pathophysiology remains unknown.
Malondialdehyde (MDA), which is a product of lipid peroxidation has been reported to be increased in certain disease conditions including preeclampsia (6, 7) which could lead to oxidative stress. Antioxidant trace elements such as selenium and zinc are essential elements incorporated into antioxidants enzymes like glutathione peroxidase and superoxide dismutase respectively to prevent oxidative stress. Meanwhile, studies have shown conflicting reports on levels of blood trace elements in preeclampsia (8–10). Preeclampsia affects women in developing countries more than women in developed nations (11), and Nigeria is known to be among the six countries in the world with very high maternal mortality rate due to preeclampsia (12). Worst still, preeclampsia and eclampsia are shown to be the leading cause of maternal mortality in Nigeria (13).
This study was therefore aimed at evaluating plasma levels of MDA and some antioxidant trace elements: selenium and zinc in preeclamptics attending antenatal visits at Chukwuemeka Odumegwu Ojukwu University Teaching Hospital in Awka, Anambra State, South East Nigeria.
Materials and Methods
Participants
This case control study evaluated the plasma levels of Selenium, Zinc and MDA in newly diagnosed preeclamptic women who have not commenced antihypertensive medications attending antenatal visits at Chukwuemeka Odumegwu Ojukwu University - Teaching Hospital (COOUTH), Awka in Anambra State from June to December 2019.
A total of 81 female participants were recruited for this study and divided into three groups (A, B and C) which comprised of 21 newly diagnosed preeclamptic women (group A), 30 pregnant control participants (group B) and 30 non-pregnant control participants (group C) . Participants aged between 20 and 35 years, preeclamptic women with minimum blood pressure of 150/100 mmHg, pregnant and non-pregnant women with normal blood pressures (<140/90 mmHg) were recruited for the study. Pregnant women with the following conditions were excluded: chronic hypertension, diabetes mellitus, thyroid diseases, liver diseases, kidney diseases and other metabolic disorders, mild hypertension, patients on mineral supplements, herbal medications and anti-hypertensives. Pregnant women with previous history of preeclampsia or eclampsia, pregnant women who did not book before 20 weeks of gestational age. Women who smoked or consumed alcohol at any gestational age of pregnancy or women with BMI>30kg/m2.
Ethical Statement
The ethical approval for this study was issued by the Ethics Committee COOUTH, Awka, Anambra state, Nigeria. Written informed consents were sought after brief explanation of the purpose of this study, and they freely signed up to participate.
Sample Collection
Five milliliters (5 ml) of random blood samples were collected from ante-cubital vein of each participant under aseptic conditions into lithium-heparin bottle. Each blood sample was centrifuged, at 3000 revolutions per minute for 5 minutes, immediately after collection at the Chemical Pathology Laboratory COOUTH. The plasma were separated into plain tubes and stored at –20oC until required for analysis. All analyses were done within two weeks of sample collection. Pregnant participants were tested for significant proteinuria using Combi 9 strips dipped in their early morning midstream urine collected in a clean universal container. Pregnancy was ruled out in non-pregnant participants by choronic gonadotrophin strips.
Laboratory Procedures
Selenium and zinc levels were determined by Atomic Absorption Spectrophotometer (AAS) according to the method of American Public Health Association (14) while MDA level was determined according to the method of Gutteridge and Wilkins (15).
Statistical Analysis
Statistical Package for Social Sciences (SSPS) version 23.0 (SPSS Inc, Chicago, IL, USA) was used in analysis of data. The results were expressed in mean±standard deviation. One way analysis of variance (ANOVA) was used for comparison of means among the three groups, post-hoc analysis was used to determine the intergroup variability, and p value<0.05 was considered to be statistically significant.
Results
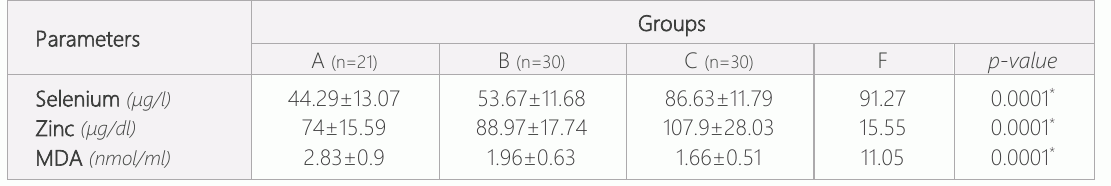
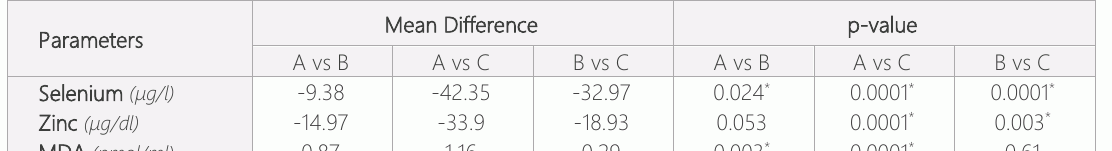
The result of this study (Tables 1&2) showed that the newly diagnosed preeclamptic women had significantly lower mean plasma level of selenium when compared to the pregnant and non-pregnant control participants (p=0.024 and 0.0001 respectively). The pregnant control also had significantly lower plasma selenium level when compared to the non-pregnant controls (p=0.0001).
There was no significant difference in the mean plasma zinc level in the newly diagnosed preeclamptic women compared to the pregnant controls (p=0.053), however, this was significantly reduced in the newly diagnosed preeclamptics when compared to the non-pregnant control participants (p=0.0001) as well as in the pregnants when compared to the non-pregnant control participants (p=0.003). The mean plasma MDA level was significantly elevated in the newly diagnosed preeclamptics in comparison to the pregnant and non-pregnants (p=0.003 and p=0.0001 respectively), however, there was no significant difference in the level of this parameter in pregnant controls when compared to the non-pregnant control participants (p=0.61).
Discussion
Preeclampsia is a life threatening complication of pregnancy which may threaten the lives of mother and/or fetus. The lower plasma selenium levels observed in preeclamptics as well as in healthy pregnant control participants may be associated with placental transfer of selenium from the mother to the developing fetus (16) as well as hemodilution resulting from increased plasma volume in pregnancy. This is in line with previous studies which also reported lower plasma selenium levels in preeclamptics (17, 18) and healthy pregnant women (19). Karita et al. (20) however reported otherwise. Venderlelie and Perkin (18) had earlier reported that an average selenium level of ≥95ug/l is required for optimal activity of the antioxidant enzyme, glutathione peroxidase (GPx), and from this study, the average plasma selenium level of preeclamptics and healthy pregnant women are suboptimal for glutathione peroxidase function. This may result to increased production of reactive oxygen species (ROS) and oxidative stress. In this study, plasma level of zinc was also significantly lower in preeclamptics compared to the non-pregnant control participants as well as in pregnant participants compared to non-pregnant participants, and this may as well be attributed to placental transfer to the growing fetus (21, 22). This is supported by studies which reported higher plasma zinc levels in fetuses compared to their mothers (23). This decrease may also be as a result of increase in plasma volume which in turn reduces plasma zinc concentration (24). Additionally, the low plasma zinc levels may be partly due to increase in urinary excretion of zinc in preeclamptics (25), and serum cortisol which is known to increase during normal pregnancy, with a much higher level in preeclampsia may as well stimulate increased zinc excretion (26). Similarly, supplemental iron of ≥65mg per day of elemental iron may decrease intestinal zinc absorption (27) or limit its bioavailability because both zinc and iron have same plasma carrier protein, transferrin. Hambidge et al. (28) showed that iron therapy in doses typically prescribed by obstetricians has an acute measurable effect on maternal zinc status. Our findings agree with the respectively reported lower levels of zinc in preeclamptics compared with non-pregnant women in Bangladesh, Saudi Arabia and India (10, 29, 30). Our finding however differs from those of Golmohammad et al. (31) and Ugwuja (32) who did not observe any significant difference in the plasma zinc levels between the preeclamptics and controls. Zinc is an essential component of the antioxidant enzyme, superoxide dismutase (SOD) involved in the removal of free radicals or ROS (33), and as such, reduction in the level of this essential element may cause insufficiency of SOD (34) thereby exposing pregnant women to oxidative stress, which may lead to the development of preeclampsia.
The elevated plasma level of MDA in preeclamptics may be due to increased generation of reactive oxygen species (ROS) which could lead to lipid peroxidation. This is consistent with reports beyond Nigeria (35)(7) and within Nigeria (36). Guptha et al. (37) however, did not demonstrate any significant difference between preeclamptics and non-pregnant controls.
Conclusion
This study suggests that preeclamptic women have lower plasma concentrations of zinc and selenium and higher MDA concentration compared to healthy pregnant and non-pregnant women. Therefore pregnant women in this environment (Nigerian Africans), especially those at high risk of developing preeclampsia, should take zinc and selenium rich diets.
Declarations
- Author contributions (CRediT)
- All authors contributed equally to all 14 CRediT roles (Conceptualization, Data curation, Formal analysis, Funding acquisition, Investigation, Methodology, Project administration, Resources, Software, Supervision, Validation, Visualization, Writing – original draft, Writing – review & editing).
- Funding
-
Funding information was not reported in the published version of this article.
- Conflicts of interest
- A conflict of interest statement was not reported in the published version of this article.
- Ethics approval
- The ethical approval for this study was issued by the Ethics Committee COOUTH, Awka, Anambra state, Nigeria. Written informed consents were sought after brief explanation of the purpose of this study, and they freely signed up to participate.
- Data availability
- A data availability statement was not reported in the published version of this article.
References (37)
21 of 37 references are linked to their DOI.
- Rudra P, Basak S, Patil D, Latoo MY. Recent advances in management of preeclampsia. Br J Medical Pract. 2011;4:9433 PubMed Google Scholar
- Magee LA, Helewa M, Pey E, von Dadelszen P. The hypertensive disorder of pregnancy. Best Pract Res Clin Obstet Gynecol. 2015;29:643-657 PubMed Google Scholar
- American College of Obstetricians and Gynaecologists. Hypertension in Pregnancy. Task Force on Hypertension and Pregnancy. 2013;1122-1133 PubMed Google Scholar
- Mc Clure EM, Saleem S, Pascha O, Goldenberg RL. Stillbirth in developing countries: A review of causes, risk factors and prevention strategies. J Matern Fetal Neonatol Med. 2009;22:183-190 PubMed Google Scholar
- Shab A, Fawole JM’Umonya. Cesearean delivery outcomes from the WHO global survey on maternal and perinatal health in Africa. Int J Gynaecol Obstet. 2009;107:191-197. PubMed Google Scholar
- Adiga U, D’Souza V, Kamath A, Mangalore N. Antioxidant activity and lipid peroxidation in preeclampsia. J Clin Med. 2007; 70:435-458 DOI Crossref PubMed Google Scholar
- Gohil JT, Patel PK, Gupta P. Evaluation of oxidative stress and antioxidant defence in subject of Preeclampsia. J Obstet Gynaecol. 2012;61:638-640 DOI Crossref PubMed Google Scholar
- Caughey AB, Stotland NE,Washington AE, Escobar GJ. Maternal ethnicity, paternal ethnicity and parental ethnic discordance: Predictors of preeclampsia in Obstetrics and Gynecology. 2005;195:148 DOI Crossref PubMed Google Scholar
- James DK, Seely PJ, Weiner CP, Gonlk B. High risk pregnancy management options 3 rd edition. Philadelphia Sauders. 2006; 920-925 PubMed Google Scholar
- Al-Jameil N, Aziz KF, Fareed Km, Tabassum H. A brief overview of preeclampsia. J Clin Med Res. 2014;6:1 -7 DOI Crossref PubMed Google Scholar
- Yaliwal RG, Taju PB, Vanishree M. Eclampsia and perinatal outcome a retrospective study in a teaching hospital. J Clin Diag. 2011;5:1056-1059 PubMed Google Scholar
- Hogan MC, Foreman KJ, Naghavi M, Ahn SY, Wang M, Makela SM, et al. Maternal mortality for 181 countries, 1980-2008: a systematic analysis of progress towards millennium development goals 5. The Lancet. 2010;375:1609-1623 DOI Crossref PubMed Google Scholar
- Oladape O, Adetoro O, Ekele B, Chama C, Etok S, Aboyeji A, Gulmezoglu A. When getting there is not enough: A nationwide cross section study of 998 maternal deaths and 1451 near-misses in public tertiary hospital in a low income country. Int J Obstet Gynecol. 2015;10:10528-13458 PubMed Google Scholar
- American Public Health Association. Direct Air-Acetylene Flame Method Standard Methods for the Examination of Metals in Blood. 20th ed. Washington DC: American Public Health Association; 1995 PubMed Google Scholar
- Gutteridge JM, Wilkins S. Copper dependent hydroxyl radical damage to ascorbic acid, formation of thiobarbituric acid reactive products. FEBS Letts. 1982;137:327 -330 DOI Crossref PubMed Google Scholar
- Olife IC, Okaka AN, Dioka CE, Meludu SC, Orisakwe OE. Iodine status and the effect of soil erosion on trace elements in Nanka and Oba towns of Anambra State Nigeria. Annals of Chemistry. 2007; 97:895-903 DOI Crossref PubMed Google Scholar
- Maleki A, Fard MK, Zadeh DH, Mamegani MA, Abasaizadeh S, Mazloomzadeh. The relationship between plasma level of Selenium and preeclampsia. Hypertension in Pregnancy. 2011; 30:180-187 DOI Crossref PubMed Google Scholar
- Vandelie J, Perkins A. Selenium and preeclampsia: A global perspective. Hypertens Pregnancy. 2011;1:213-224 PubMed Google Scholar
- Nwagha UI, Ogbodo SO, Nwogu-Ikojo EE, Ibegbu DM, Ejezie FE, Nwagha TU, et al. Copper and selenium status of healthy pregnant women in Enugu, Southeastern Nigeria. Nig J Clin Pract. 2011;14:408-412 DOI Crossref PubMed Google Scholar
- Karita K, Takano T, Satoh K.Variations in plasma selenium levels as a result of the menstrual cycle and pregnancy in healthy Japanese women. Biol Trace Elem Res. 2004; 99:83 DOI Crossref PubMed Google Scholar
- Garg HK, Singhai KC and Arshad. A study of the effect of oral zinc supplementation during pregnancy on outcome. Indian J Physiol Pharmacol. 1993;37:276-284 PubMed Google Scholar
- Tamura T, Goldenberg RL, Johnston KE, Dubard M. Maternal plasma zinc concentrations and pregnancy outcome. Am J Clin Nutr. 2000;71:109-113 DOI Crossref PubMed Google Scholar
- Caulfield LE, Zavaleta N, Figuena A, Leon Z. Zinc supplementation does not affect size at birth or pregnancy duration in Peru. J Nutr. 1998;129:1567-1568 DOI Crossref PubMed Google Scholar
- Swanson CA and King JC. Zinc and pregnancy outcome. Am J Clin Nutr. 1987;46:763-771 DOI Crossref PubMed Google Scholar
- Moyene JE, Scheers H, Jandumba, Haufroid V, Buassa-bu-Tsumbu B, Verdonck F, Spitz B, et al. Preeclampsia and toxic metal. A case control study in Kinshana DR Congo. Environ Health. 2016;15:48 PubMed Google Scholar
- Milne DB, Carel AB, Edward RA, Tietz. Textbook of Clinical Chemistry.3 rd Edition. Saunders Company. 1999;1029-1041 PubMed Google Scholar
- O’Brien KO, Zaraleta N, Caulfield LE, Wen J, Abrams SA. Prenatal iron supplement, impair zinc absorption in pregnant Perovian women. J Nutr. 2000; 130:2251-2255 DOI Crossref PubMed Google Scholar
- Hambidger K, Krebs NF, Sibley L, English L. Acute effects of iron therapy on zinc status during pregnancy. Obstet Gynaecol. 1987;70:593-596 DOI Crossref PubMed Google Scholar
- Jain S, Sharma P, Kulshreshtha S, Mohen G, Singh S. The role of calcium, magnesium and zinc in preeclampsia. Biol Trace Elem Res. 2010;133:162-170 DOI Crossref PubMed Google Scholar
- Sarwar MS, Ahmed S, Ullah MS, Kabir H, Rahmar GK, Hasnat A, et al. Comparative study of serum, zinc, copper, manganese and iron in prepregnant women. Biol Trace Elem Res. 2013;154:14-20 Preeclamptic Women Ilechukwu et al. DOI Crossref PubMed Google Scholar
- Golmohammad, Lou S, Amivahi A, Yazdian M, Pashapur N. Evaluation of serum calcium, magnesium, copper and zinc levels in women with preeclampsia. Iranian J Med Sci. 2008; 33:235-238 PubMed Google Scholar
- Ugwuja EI, Ejikeme BN, Ugwuja NC, Obeka NC, Akubugwo EI, Obidoa O. Comparison of plasma copper, iron and zinc levels in hypertensive and non-hypertensive pregnancy women in Abakaliki, South East Nigeria. Pakistan J Nutr. 2010;9:1136-1140 DOI Crossref PubMed Google Scholar
- Chan S, Gerson B, Subraman IM. The role of copper, molybdenum, selenium and zinc in nutrition and health. Clin Lab Med. 1998;18:673-685 DOI Crossref PubMed Google Scholar
- Acikgoz S, Harma M, Harma M, Mongan G, Can M, Demirtas. Comparison of angiotensin converting enzyme, MDA, zinc and copper levels in preeclampsia. Biol Trace Elem Res. 2006;113:1-8 DOI Crossref PubMed Google Scholar
- Patil SB, Kodiwadmath MV, Kadiwadmath SM. Role of lipid peroxidation and enzymatic antioxidants in pregnancy induced hypertension. Clin Exp Obstet Gynaecol. 2007;34:239-241 PubMed Google Scholar
- Nnodim J, Ihim A, Uduji HI. Alterations in antioxidant Enzyme and Malondialdehyde status in preeclampsia. Asian Pac J Trop Biomed. 2012;5750-5752 PubMed Google Scholar
- Guphta A, Kant S, Gupta SK, Prakash S, Kalaivani M, Pandav CS, et al. Serum FRAP levels and preeclampsia among pregnant women in a rural community of Northern India. J Clin Diag Res. 2016;102:12-15 DOI Crossref PubMed Google Scholar
Respond to this article
Comments on a published article are welcome as a Letter to the Editor.
Get an e-mail when new articles in your fields are published
Questions to the authors
Questions are moderated: an editor approves each question, the authors answer, and an editor approves the answer before both appear here.
No answered questions yet.
Ask the authors a question
Discussion
Comments are moderated: they appear after the writer confirms the e-mail address and an editor approves them. Each comment carries a conflict-of-interest statement.
No comments yet.
Write a comment
Read the full text
Open the PDF here
Loading the PDF…
If the PDF does not show here, use the download button above.
How to cite this article
Ilechukwu OU, Onuegbu JA, Olisekodiaka JM, Obi-Ezeani CN. Evaluation of Plasma Selenium, Zinc and Malondialdehyde Levels in Newly Diagnosed Preeclamptic Women at A Teaching Hospital. Ulutas Med J. 2021;7(2):86-91. doi:10.5455/umj.20210422011242
Ilechukwu, O. U., Onuegbu, J. A., Olisekodiaka, J. M., & Obi-Ezeani, C. N. (2021). Evaluation of Plasma Selenium, Zinc and Malondialdehyde Levels in Newly Diagnosed Preeclamptic Women at A Teaching Hospital. The Ulutas Medical Journal, 7(2), 86–91. https://doi.org/10.5455/umj.20210422011242
Ilechukwu, O.U. et al. (2021) 'Evaluation of Plasma Selenium, Zinc and Malondialdehyde Levels in Newly Diagnosed Preeclamptic Women at A Teaching Hospital', The Ulutas Medical Journal, 7(2), pp. 86–91. doi: 10.5455/umj.20210422011242.
@article{umj75583,
  title = {Evaluation of Plasma Selenium, Zinc and Malondialdehyde Levels in Newly Diagnosed Preeclamptic Women at A Teaching Hospital},
  author = {Ilechukwu, Obianuju Uchenna and Onuegbu, Jude Anaelechi and Olisekodiaka, Japhet Madu and Obi-Ezeani, Chikaodili Nwando},
  journal = {The Ulutas Medical Journal},
  year = {2021},
  volume = {7},
  number = {2},
  pages = {86--91},
  doi = {10.5455/umj.20210422011242},
  url = {https://www.ulutasmedicaljournal.com/?mno=75583},
  issn = {2149-388X}
}